

MT200605 II期临床达主要终点!这款脑梗在研新药为何入选国家科技重大专项?
MICOT
点击蓝字 关注我们

Slide to view different languages
滑动查看不同语言
近日,麦科医药(2335.HK)自主研发的注射用神经保护候选药物MT200605,在治疗急性缺血性脑卒中(脑梗)的II期临床试验中,成功达到主要研究终点。
这是一次基于科学设计、经过严格临床验证的探索。在脑梗治疗领域,临床上长期存在两大痛点:一部分患者血管成功再通,但神经功能仍难以恢复;还有大量患者无法实现血管再通,缺乏有效的治疗手段。MT200605的临床数据为此类患者提供了极具价值的解决方案。
就在今年5月,MT200605入选了“创新药物研发国家科技重大专项”,这是对其创新设计的高度认可,也意味着MT200605的临床推进被纳入了国家解决心脑血管疾病关键科技问题的战略布局中。

脑梗之殇:全球每4秒一例,血管再通为何不等于康复?
脑梗(缺血性卒中)是因脑血管堵塞导致脑组织缺血缺氧的急症,具有高发病率、高致残率、高死亡率的特点。全球疾病负担研究显示,2021年全球新发缺血性卒中约780万例,平均每4秒就有一人发病。而中国是卒中负担最重的国家之一。
目前,静脉溶栓和机械取栓是急性期最有效的治疗手段,能够快速开通闭塞血管、恢复脑组织血流。但临床上,一个令人痛心的现象普遍存在:不少患者血管成功再通了,语言、肢体活动能力却没能同步恢复。这就是“临床无效再灌注”。因为血管堵塞只是脑梗发病的起点,血流中断后,脑组织中爆发的氧化应激、炎症瀑布、神经元凋亡等一系列脑组织的继发性损伤,才是决定患者能否重新开口说话、独立行走的关键。
还有一个事实我们不得不面对:临床上,仅有9.4%的发病患者接受了静脉溶栓,意味着大部分脑梗患者在发病后没有接受到溶栓治疗。

因为溶栓药物有严格的时间窗限制,通常要求在发病4.5小时内使用;取栓手术的时间窗稍长,但也大多要求在6到24小时内完成。再加上患者本人及家属对脑梗症状的识别延迟、赶到医院所需的时间、医院资质和设备等条件的限制,真正能赶在时间窗内完成血管再通的患者非常少。
这意味着,大多数脑梗患者,只能依靠常规的保守治疗——抗血小板药物、控制血压血糖、基础营养神经支持,然后等待大脑自己恢复。保守治疗不是不管用,而是太被动。它缺少一个能够主动干预脑梗后“细胞崩溃”的机制。这正是脑梗的致残率依然居高不下的根本原因之一,更是全球神经保护药物数十年来探索的核心目标,MT200605瞄准的就是这个关键突破口——无论患者血管是否成功再通,均有望发挥治疗价值。

现有神经保护药物尚无I级推荐/A类证据
目前临床上常用的神经保护类药物,作用靶点相对集中在止损、阻断缺血级联反应:
有的主要作用于改善微循环和线粒体功能,覆盖缺血级联反应的上游及部分中游环节。
有的主要作为自由基清除剂,作用于氧化应激这一中游环节。
还有的在清除自由基的基础上增加抗炎作用,覆盖中游的两个靶点。
这些药物可在卒中后使用,为患者提供了治疗选择,但临床获益仍有提升空间——《中国急性缺血性卒中诊治指南2023》尚无一级推荐、A级证据的神经保护剂,意味着神经保护领域仍存在巨大未被满足的需求。
MT200605:国家科技重大专项为何选中它?
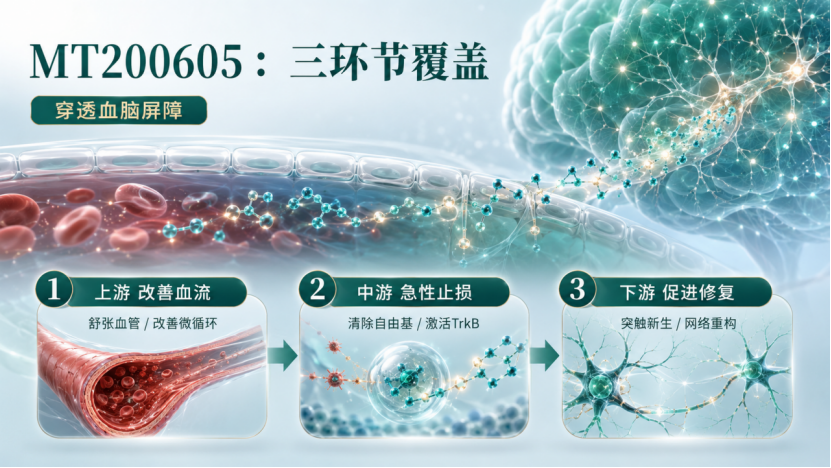
MT200605的独特之处,首先在于其能够高效穿透血脑屏障。血脑屏障是大脑的一道天然“城墙”,阻挡血液中的有害物质进入脑组织,但也正因如此,绝大多数药物无法进入大脑发挥作用——这也是过去很多神经保护药物在实验室有效、到临床上却失败的重要原因之一。MT200605作为一款小分子静脉注射液,能够真正“抵达战场”,在脑组织内部直接发挥保护与修复作用。
在此基础上,MT200605不同于现有药物多局限于单一靶点,而是一个分子在脑梗的发病进程中同时覆盖上游改善血流、中游急性止损、下游促进修复的三个关键环节:
01
上游改善血流:通过阻断血管平滑肌钙离子信号通路而舒张血管,解除微血管痉挛导致的继发性缺血,改善微循环,改善脑部供血。
02
中游急性止损:强力清除氧自由基,阻断氧化应激损伤;同时激动TrkB受体,抑制神经元凋亡和兴奋性毒性,加速清除氧自由基,在“缺血半暗带”(脑梗死核心周围“半死不活”的区域)抢救濒死的神经细胞。
03
下游促进修复:持续激活TrkB通路,相当于补充了脑内天然存在的“脑源性神经营养因子(BDNF)”功能,启动突触新生、轴突再生、神经网络重构等内源性修复程序,为患者后续功能恢复打下基础。
目前所有进入临床阶段的缺血性卒中治疗药物中,MT200605是唯一能够穿透血脑屏障、靶向BDNF/TrkB通路、具有神经营养作用的小分子激动剂。
这些独特性,使其有望填补“神经营养修复”领域的临床空白,也是其获得国家科技重大专项青睐的关键。
不止于脑梗:罕见病领域同样获得认可
值得一提的是,MT200605的潜力不仅限于缺血性脑卒中。其能够选择性激活TrkB信号通路,发挥神经保护及抗氧化双重作用在神经退行性疾病领域同样具有应用前景。
临床前研究显示,MT200605具有直接减少突变亨廷顿蛋白聚集的潜力,有望为亨廷顿舞蹈病提供一种具有疾病修正作用的治疗策略。基于此,MT200605已于2026年3月正式获得美国食品药品监督管理局(FDA)授予的亨廷顿舞蹈病孤儿药资格认定。
这一国际监管认可,从侧面验证了MT200605作用机制的科学性和创新性,也为其在更广泛神经系统疾病领域的探索打开了空间。
从基础研究到临床验证:II期数据的意义
此次MT200605达到主要终点的II期临床试验,是一项多中心、随机、双盲、安慰剂对照研究,共入组360名受试者。

有效性方面,主要疗效终点为90天mRS 0-1分的患者比例。mRS(改良Rankin量表)是国际通用的卒中后功能评估工具,0-1分代表患者虽有症状但无明显功能障碍,能完成日常事务。
结果显示,MT200605中、高剂量组达到mRS 0-1分的比例均高于安慰剂组,其中高剂量组较安慰剂组疗效优势提高100%以上,组间差异具有显著统计学意义。
通俗来说,“统计学意义”意味着这一差异并非偶然因素导致,而是药物干预带来的真实效果,为后续临床开发提供了可靠的决策依据。次要疗效终点也呈现同样的有效性趋势。
在安全性方面,MT200605安全性、耐受性良好,整个研究期间未发生与试验药物相关的严重不良事件(SAE),≥3级的治疗期间不良事件(TEAE)在各组间均衡,未发现新的安全性风险信号。
40年前,诺贝尔奖得主发现了神经生长因子(NGF),为神经修复研究打开了一扇门。今天,麦科医药正通过MT200605,将科学探索转化为临床验证。
此次II期临床达到主要终点,是MT200605研发路上的重要里程碑,更是为千万脑梗患者和家庭带来新希望的关键一步。
麦科医药将加速推进后续临床开发,让这款承载国家使命、兼具国际认可的创新药,早日惠及患者。
MICOT

MT200605, an investigational neuroprotectant for injection independently developed by Shaanxi Micot Pharmaceutical Technology Co., Ltd. (“Micot Pharma”; 2335.HK), recently met the primary endpoint in a Phase II trial in acute ischemic stroke (AIS).
The result reflects a scientifically grounded design and rigorous clinical validation. Two major unmet needs have long persisted in ischemic stroke care: some patients achieve successful recanalization but fail to recover neurological function, while many others do not achieve recanalization and lack effective treatments. The clinical data for MT200605 offer a potentially valuable therapeutic option for these patients.
In May 2026, MT200605 was selected for the National Science and Technology Major Project for Innovative Drug Development. The selection recognizes its innovative design and incorporates its clinical development into China’s strategic effort to address key scientific and technological challenges in cardiovascular and cerebrovascular diseases.

The Toll of Ischemic Stroke: One New Case Every Four Seconds—Why Does Recanalization Not Mean Recovery?
Ischemic stroke is an acute emergency caused by cerebrovascular occlusion, which deprives brain tissue of blood and oxygen. It has high incidence and high rates of disability and mortality. According to the Global Burden of Disease Study, approximately 7.8 million new ischemic strokes occurred worldwide in 2021—one every four seconds. China has one of the world’s heaviest stroke burdens.
Intravenous thrombolysis and mechanical thrombectomy are currently the most effective acute treatments, rapidly reopening occluded vessels and restoring cerebral blood flow. Yet a distressing problem remains common: even after successful recanalization, many patients fail to recover speech or motor function. This is known as “futile reperfusion.”
Vascular occlusion is only the initial event in ischemic stroke. Once blood flow is interrupted, secondary brain injury—including oxidative stress, inflammatory cascades and neuronal apoptosis—is triggered. These processes largely determine whether patients can speak again or walk independently.
Another reality must be acknowledged: only 9.4% of patients receive intravenous thrombolysis, meaning that most patients do not receive thrombolytic treatment after stroke onset.
Thrombolytic agents have a strict treatment window and generally must be given within 4.5 hours of symptom onset. Mechanical thrombectomy has a longer window but must still usually be performed within 6–24 hours. Delayed symptom recognition by patients and families, transport time, and limitations in hospital capabilities and equipment mean that few patients achieve recanalization within these windows.
Most patients therefore rely on standard medical management—antiplatelet therapy, blood pressure and glucose control, and basic neurotrophic support—while waiting for the brain to recover.
Standard medical management is not ineffective, but it is passive. It lacks a mechanism that actively interrupts post-stroke cellular injury. This is a major reason disability rates remain high and has been a central target of neuroprotective drug research for decades.
MT200605 targets this critical gap and may provide therapeutic value whether or not successful recanalization is achieved.
No Existing Neuroprotective Agent Has a Class I Recommendation Supported by Level A Evidence
Neuroprotectants currently used in clinical practice mainly limit injury by interrupting the ischemic cascade:
Some improve microcirculation and mitochondrial function, targeting upstream and some midstream processes.
Some act mainly as free-radical scavengers, targeting midstream oxidative stress.
Others combine free-radical scavenging with anti-inflammatory activity, targeting two midstream processes.
These drugs can be used after stroke and provide treatment options, but their clinical benefit could be further improved. The Chinese Guidelines for the Diagnosis and Treatment of Acute Ischemic Stroke 2023 give no neuroprotectant a Class I recommendation supported by Level A evidence,highlighting the substantial unmet need in neuroprotection.
MT200605: Why Was It Selected for a National Science and Technology Major Project?
A defining feature of MT200605 is its ability to efficiently cross the blood–brain barrier.
The blood–brain barrier is a natural defense that prevents harmful blood-borne substances from entering brain tissue. However, it also prevents most drugs from reaching the brain in sufficient concentrations. This is one reason many neuroprotective candidates have been effective in laboratory studies but failed clinically.
As a small-molecule intravenous formulation, MT200605 can reach brain tissue and act directly at the site of injury.
Unlike many existing drugs limited to a single target, MT200605 uses one molecule to address three key stages of ischemic stroke: improving upstream blood flow, limiting acute midstream injury and promoting downstream repair.
01
Upstream—improving blood flow: By inhibiting calcium signaling in vascular smooth muscle, MT200605 induces vasodilation, relieves secondary ischemia caused by microvascular spasm, improves microcirculation and enhances cerebral perfusion.
02
Midstream—limiting acute injury: MT200605 potently scavenges reactive oxygen species (ROS), limiting oxidative injury. It also activates TrkB to inhibit neuronal apoptosis and excitotoxicity and further enhance ROS clearance, helping rescue threatened neurons in the ischemic penumbra—the potentially salvageable tissue surrounding the infarct core.
03
Downstream—promoting repair: Sustained TrkB activation mimics the function of endogenous brain-derived neurotrophic factor (BDNF), initiating repair programs including synaptogenesis, axonal regeneration and neural network remodeling, and supporting subsequent functional recovery.
Among ischemic stroke therapies currently in clinical development, MT200605 is the only small-molecule agonist that crosses the blood–brain barrier, targets the BDNF/TrkB pathway and has neurotrophic activity.
This profile may fill a clinical gap in neurotrophic repair and was central to its selection for the National Science and Technology Major Project.
Beyond Ischemic Stroke: Recognition in Rare Disease Development
MT200605’s potential extends beyond ischemic stroke. Its selective activation of TrkB signaling and dual neuroprotective and antioxidant actions also support its development in neurodegenerative diseases.
Preclinical studies suggest that MT200605 may directly reduce mutant huntingtin protein aggregation, offering a potentially disease-modifying treatment strategy for Huntington’s disease.
Based on these findings, the U.S. Food and Drug Administration (FDA) granted MT200605 Orphan Drug Designation for Huntington’s disease in March 2026.
This international regulatory recognition indirectly supports the scientific rationale and novelty of its mechanism and opens opportunities to explore MT200605 in a broader range of neurological diseases.
From Basic Research to Clinical Validation: The Significance of the Phase II Results
The Phase II trial in which MT200605 met its primary endpoint was a multicenter, randomized, double-blind, placebo-controlled study involving 360 participants.
The primary efficacy endpoint was the proportion of patients achieving a modified Rankin Scale (mRS) score of 0–1 at Day 90. The mRS is an internationally accepted measure of post-stroke functional outcomes. A score of 0–1 indicates no significant functional disability and the ability to perform usual activities despite possible symptoms.
Both the medium- and high-dose MT200605 groups had higher proportions of patients achieving an mRS score of 0–1 than the placebo group. In the high-dose group, the relative efficacy advantage versus placebo exceeded 100%, with a statistically significant between-group difference.
In practical terms, statistical significance indicates that the difference is unlikely to be due to chance and supports a treatment effect, providing a reliable basis for further clinical development. Secondary efficacy endpoints showed consistent trends.
MT200605 was well tolerated and showed a favorable safety profile. No treatment-related serious adverse events (SAEs) occurred during the study. Grade ≥3 treatment-emergent adverse events (TEAEs) were balanced across groups, and no new safety signals were identified.
Forty years ago, the Nobel Prize recognized the discovery of nerve growth factor (NGF), opening a new chapter in neural repair research. Today, Micot Pharma is translating scientific research into clinical validation through MT200605.
Meeting the primary endpoint in this Phase II trial is an important milestone in the development of MT200605 and a critical step toward bringing new hope to millions of patients with ischemic stroke and their families.
Micot Pharma will accelerate further clinical development so that this innovative therapy—supported by a national strategic program and international regulatory recognition—can benefit patients as soon as possible.
MICOT
详情
奋斗为本、求是创新、协作共赢
